Carta científica
Vol. 4 Núm. 3 (English)
8 min
Is Ipratropium Bromide useful in children with moderate asthma exacerbation?
¿Es útil el bromuro de ipratropio en niños con crisis asmática moderada?
Irene Comino-Hidalgo*, Francisco Javier Brincau-García, Irene Gil-Ángel, María Escobar-Castellanos, Rafael Marañón, Ana Jové-Blanco
1Gregorio Marañón General University Hospital, Madrid, Spain
Correspondencia:
Recepción:
08/07/2025
Aceptación:
10/09/2025
Publicación:
16/12/2025
Métricas
200
Visualizaciones
16
Descargas
Compartir
Compartir
Resumen (ES)
Introducción: persiste la controversia sobre la combinación del bromuro de ipratropio (BI) con el tratamiento del asma en niños.
Objetivo: examinar las diferencias en los resultados del asma moderada —tasa de ingreso, estancia en el SUP, Pulmonary Score y reconsultas— tras la suspensión del BI.
Métodos: estudio de cohorte retrospectivo, unicéntrico. Se incluyeron pacientes de 6 a 16 años que acudieron al SUP con crisis asmática moderada (Pulmonary Score [PS]: 4-6). Se examinaron los registros en dos periodos: Cohorte 1 recibió salbutamol, ipratropio y glucocorticoides sistémicos (01/09/2018–01/09/2019); Cohorte 2 recibió salbutamol y glucocorticoides sistémicos (01/09/2021– 01/09/2022). Se evaluó la asociación del uso de BI con los desenlaces: tasa de ingreso y reconsultas (Chi cuadrado), estancia en el SUP y Pulmonary Score al alta (prueba t de Student). Se analizaron variables y predictores de ingreso mediante análisis multivariable.
Resultados: se incluyeron 351 pacientes: 174 (49,6 %) en la Cohorte 1 y 177 (50,4 %) en la Cohorte 2. El BI no se asoció con cambios en la tasa de ingreso (15 [8,6 %] en la Cohorte 1 frente a 7 [4 %] en la Cohorte 2; p=0,07), la estancia media en el SUP (2,33 horas [DE: 0,66] frente a 2,46 horas [DE: 0,85]; p=0,207), el Pulmonary Score al alta (0,78 [DE: 0,85] frente a 0,92 [DE: 0,79]; p=0,137) ni las reconsultas (25 [14,5 %] frente a 14 [7,9 %]; p=0,052).
Conclusión: el bromuro de ipratropio no parece aportar beneficios en las exacerbaciones asmáticas moderadas.
Palabras clave (ES):
Resumen (EN)
Introduction: controversy surrounds combining ipratropium bromide (IB) with asthma treatment in children.
Objective: Examine differences in moderate asthma outcomes: admission rate, PED stay, Pulmonary Score, and revisits post discontinuing IB.
Methods: single-center, retrospective, cohort study. Patients from 6 to 16 years who attended the PED with moderate asthmatic crisis (Pulmonary Score [PS]: 4-6) were included. Examined records in two periods: Cohort 1 received salbutamol, ipratropium, systemic glucocorticoids (01/09/2018-01/09/2019). Cohort 2 had salbutamol, systemic glucocorticoids (01/09/2021-01/09/2022). Evaluated the association of IB use with outcomes: admission rate, revisits (Chi-square), PED stay, and PS score at discharge (Student’s T test). Analyzed variables and predictors for admission using multivariable analysis.
Results: 351 patients were included: 174 (49.6%) in Cohort 1 and 177 (50.4%) in Cohort 2. IB was not associated with admission rate (15 [8.6%] in Cohort 1 vs 7 [4%] in Cohort 2; p0.07), median stay in the PED (2.33hours [SD:0.66] vs 2.46 hours [SD:0.85], p0.207), Pulmonary Score at discharge (0,78 [SD:0.85] vs 0,92 [SD:0.79]; p0.137) nor revisits (25 [14,5%] vs 14 [7,9%]; p0.052); p0.207).
Conclusion: IB does not seem useful in moderate asthmatic exacerbations.
Palabras clave (EN):
Asthma exacerbations account for approximately 5% of visits to Pediatric Emergency Departments (PED), a figure that rises to 15% during the autumn season(1). However, ongoing controversy exists regarding the optimal treatment for moderate asthma exacerbations in the emergency setting(2,3).
According to the most recent Spanish asthma guidelines (GEMA 5.5, 2025), the recommended treatment for moderate asthma exacerbations in children consists of short-acting beta-2 agonists (SABA), such as salbutamol, combined with systemic corticosteroids. Ipratropium bromide (IB) is not included as part of the standard treatment protocol(2). Furthermore, the Global Initiative for Asthma (GINA 2025) classifies IB as an optional adjunct therapy (level B recommendation) for patients with moderate exacerbations, but its use is not mandatory(3).
In this context, standardized treatment for moderate asthma exacerbations in our PED changed in 2021. Before 2021, moderate exacerbations were treated with oral glucocorticoids and inhaled bronchodilators (SABA and IB). After 2021, IB was no longer used as standardized treatment(8).
The primary objective of this study was to analyze the impact of removing IB from the standardized management of moderate asthma exacerbations in our PED, with regard to hospitalization rates. Secondary objectives included comparing pulmonary scores (PS) at discharge, length of stay in the PED, and revisit rates.
A retrospective, single-center cohort study was conducted in the PED of a tertiary hospital with 60,000 annual visits.
Two cohorts were analyzed. Cohort 1 (September/2018– September/2019): patients received oral corticosteroids, salbutamol, and IB. Cohort 2 (September/2021–September/2022): patients received oral corticosteroids and salbutamol. Updated treatment guidelines were distributed among clinical staff. Data were obtained from electronic medical records. The study was approved by the institutional ethics committee.
All patients aged 6 to 16 years who visited the PED with moderate asthma exacerbation during the predefined study periods were included. Asthma exacerbation was defined as an episode characterized by dyspnea, respiratory difficulty, chest tightness, cough, and wheezing. The pulmonary score (PS) was used to grade the severity of the exacerbation. A moderate asthma exacerbation was defined as a PS between 4 and 6 points and a peripheral oxygen saturation above 90%(2).
Patients who did not receive treatment according to the protocol in place during each study period were excluded. Those who did not receive oral glucocorticoids or who had received nebulized bronchodilators were also excluded.
Statistical analysis was performed using IBM SPSS Statistics version 25.0 (IBM Corp., Chicago, Illinois, USA). Quantitative variables were expressed as median and interquartile range. Qualitative variables were expressed as percentages. The chi-square test was used for comparative analysis of qualitative variables, and the Mann-Whitney U test was used for quantitative variables. A multivariate logistic regression model was performed to assess possible associations between variables and predictors of hospitalization. Results with p < 0.05 were considered statistically significant.
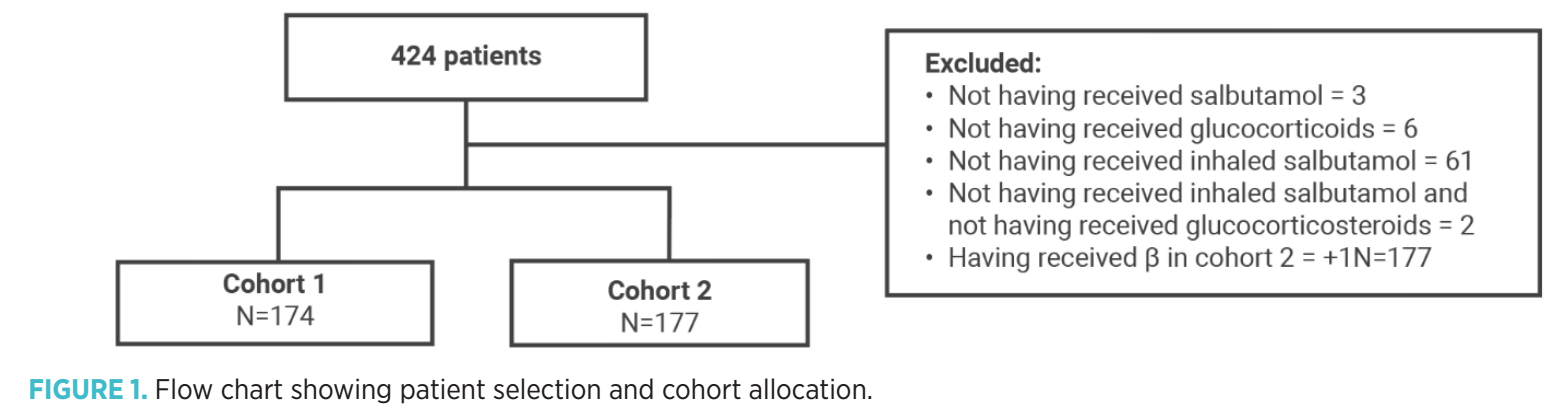
A total of 424 patients were initially selected, of whom 73 were excluded. The final sample included 351 patients: 174 (49.6%) in Cohort 1 and 177 (50.4%) in Cohort 2 (Figure 1). Baseline characteristics of both cohorts are shown in Table 1.
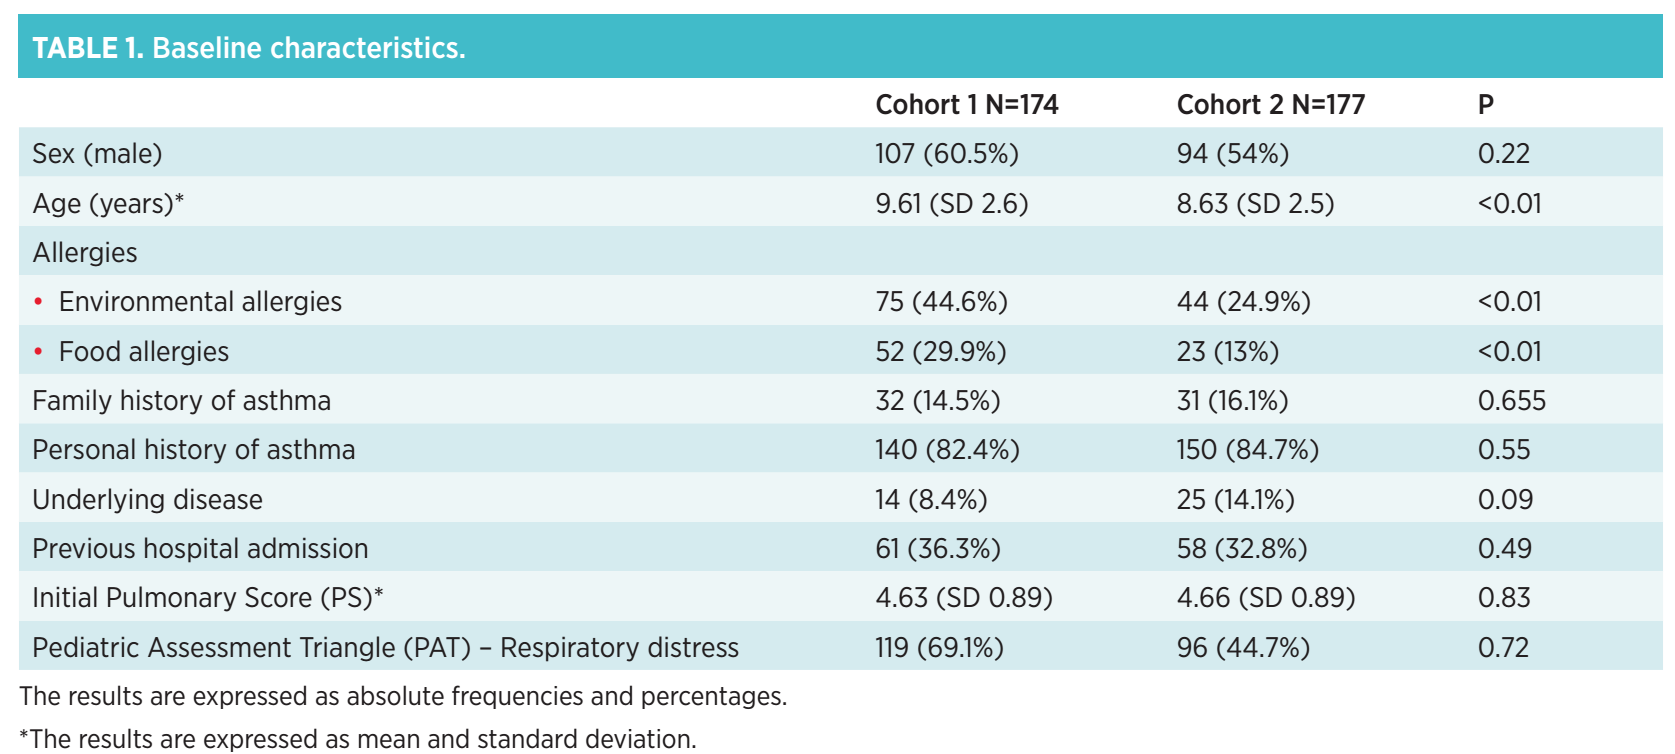
No significant differences were observed in hospitalization rates between Cohort 1 (15 patients, 8.6%) and Cohort 2 (7 patients, 4%) (p = 0.07). There were also no significant differences in PS at discharge (0.78 points [SD 0.85] in Cohort 1 vs. 0.92 points [SD 0.79] in Cohort 2; p = 0.137), length of stay in the PED (2.33 h [SD 0.66] vs. 2.33 h [SD 0.85]; p = 0.207), or revisit rates (14.5% vs. 7.9%; p = 0.052).
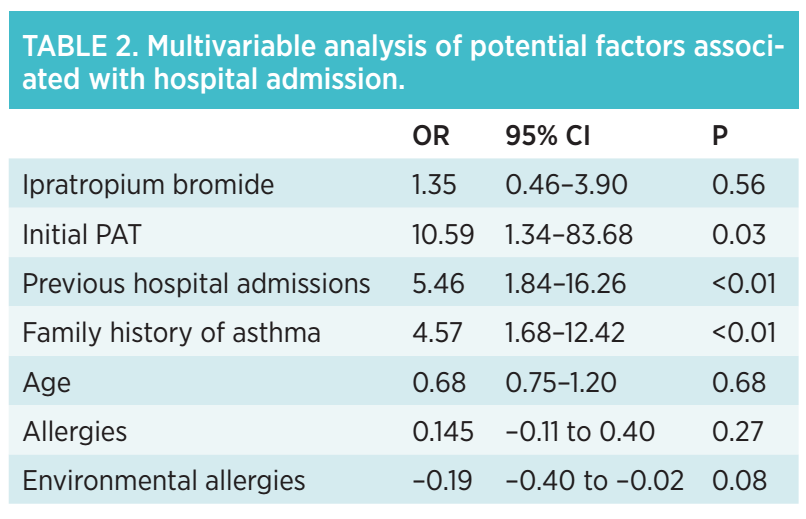
In the multivariable analysis, not using IB was not associated with an increased risk of hospitalization (Table 2). However, an altered PAT score during the first evaluation, previous hospital admissions, and a family history of asthma were associated with a higher hospitalization risk (Table 2).
Our study analyzes the impact of excluding IB from the standardized treatment of moderate asthma exacerbations. The findings indicate that the use of IB did not influence hospitalization rates, PS at discharge, length of stay, nor revisit rates.
Evidence regarding the use of IB in moderate asthma exacerbations has evolved. Some studies(4) reported reduced hospitalization rates when IB was added to short-acting beta agonists in moderate or severe exacerbations, whereas others(5,6,7) found no benefit of IB use in moderate cases. These findings are consistent with our results and support the most recent national and international recommendations(2,3).
In our research, we did not observe differences in PS scores at discharge. Previous studies(8,9) reported non-significant clinical improvements with the addition of IB in moderate asthma exacerbations. Iramain et al.(5) suggested benefits in respiratory parameters (oxygen saturation, pulmonary score, %FEV1, and %PEF), mainly in severe exacerbations.
Other studies (10–12) have focused on the impact of adding IB on hospital length of stay, showing that IB does not reduce admission duration. However, no prior literature exists regarding its impact on PED length of stay. In our study, we did not observe differences between cohorts for this outcome. Additionally, unlike previous literature, our study evaluated revisit rates and found no significant differences. Only Cooper et al.(4) reported that IB does not appear to reduce the risk of recurrent asthma exacerbations.
Multiple factors increase the risk of hospitalization among children presenting to the PED with moderate asthma exacerbation, such as exposure to environmental pollutants, previous hospitalizations for asthma exacerbations, or greater severity of symptoms on arrival(14). In our study, Cohort 1 showed a proportionally higher, although non-significant, number of hospitalizations. In multivariable analysis, this increase was not associated with IB use, but rather with the presence of respiratory distress on initial PAT assessment. It was also associated with prior hospitalization episodes, consistent with the literature(15).
This study has several limitations. Its retrospective and single-center design may introduce selection and information bias, limiting the generalizability of findings. The study was conducted two years after the change in treatment protocol; therefore, other uncontrolled factors (e.g., environmental exposures) may have influenced results. Additionally, the impact of the COVID-19 pandemic during the second study period cannot be fully excluded. Finally, the analysis was limited to short-term outcomes, with no long-term follow-up.
Despite its limitations, the clearly defined inclusion criteria and relatively large sample size support its internal validity. The results reinforce current recommendations and clarify the limited role of IB in moderate asthma exacerbations. Avoiding routine IB use may reduce adverse effects(13) and simplify treatment. Although the findings provide useful clinical information, they may not be generalizable to all settings and should be interpreted with caution. Prospective, randomized, multicenter studies are needed to confirm these results.
In conclusion, ipratropium bromide does not appear to provide additional benefit in moderate asthma exacerbations. Treatment with salbutamol and corticosteroids alone is effective and aligned with current guidelines.
Ethical statement
This study was approved by the hospital’s Ethics and Clinical Research Committee in September 2022.
Conflicts of interest and funding sources
All authors declare no conflicts of interest related to the manuscript, including financial, consulting, institutional, or other relationships that could create bias or conflict of interest.
Meetings where the work was presented
The study was presented as an oral communication at the XXVII Meeting of the Spanish Society of Pediatric Emergency Care in May 2023.
The investigation was conducted in accordance with the ethical standards outlined in the 1964 Declaration of Helsinki and its subsequent amendments, or comparable ethical guidelines.
References
- Paniagua N, Fernández B. Diagnosis and treatment of asthmatic crisis in the emergency department. Protoc Diagn Ter Pediatr. 2020;1:49–61. [Consulted 28 Mar 2023]. Available from: https://www.aeped.es/protocolos/
- Almonacid C, Blanco M, Ferreira J, García G, Morete A, Quirce S, et al. Key updates in the 2025 Spanish Asthma Guidelines (GEMA 5.5). Open Respir Arch.2025;7(3):100453. Available from: https://doi.org/10.1016/j.opresp.2025.100453
- Global Initiative for Asthma. Global strategy for asthma management and prevention, 2025 update. May 2025. Available from: https://ginasthma.org
- Cooper DD, Welch JL. Should children with acute asthma exacerbation receive inhaled anticholinergics? Ann Emerg Med. 2015;65:83–4.
- Iramain R, López-Herce J, Coronel J, Spritters C, Guggiari J, Bogado N. Inhaled salbutamol plus ipratropium in moderate and severe asthma crises in children: a prospective randomized double-blind clinical trial. J Asthma. 2011;48(3):298–303.
- Wyatt EL, Borland ML, Doyle SK, Geelhoed GC. Metered-dose inhaler ipratropium bromide in moderate acute asthma in children: a single-blinded randomised controlled trial. J Paediatr Child Health. 2015;51(2):192–8.
- Xu H, Tong L, Gao P, Hu Y, Wang H, Chen Z, et al. Combination of ipratropium bromide and salbutamol in children and adolescents with asthma: a meta-analysis. Pediatr Pulmonol. 2021;56(7):2008–18. Available from: https://doi.org/10.1002/ppul.25426
- Memon BN, Parkash A, Ahmed Khan KM, Gowa MA, Bai C. Response to nebulized salbutamol versus combination with ipratropium bromide in children with acute severe asthma. J Pak Med Assoc. 2016;66:243–6.
- Dotson K, Dallman M, Bowman CM, Titus MO. Ipratropium bromide for acute asthma exacerbations in the emergency setting: a literature review of the evidence. Pediatr Emerg Care. 2009;25(11):687–92.
- Murphy K, Mahmood N, Craven D, Gallagher J, Ross K, Speicher R, et al. Randomized pilot trial of ipratropium versus placebo in children with critical asthma. Pediatr Pulmonol. 2020;55(11):3287–92. Available from: https://doi.org/10.1002/ppul.25049
- Craven D, Kercsmar CM, Myers TR, O'Riordan MA, Golonka G, Moore S. Ipratropium bromide plus nebulized albuterol for the treatment of hospitalized children with acute asthma. J Pediatr. 2001;138(1):51–8.
- Goggin N, Macarthur C, Parkin PC. Randomized trial of the addition of ipratropium bromide to albuterol and corticosteroid therapy in children hospitalized because of an acute asthma exacerbation. Arch Pediatr Adolesc Med. 2001;155(12):1329–34.
- U.S. Food and Drug Administration. Technical data for Ipratropium Bromide [Consulted 20 Jul 2025]. Available from: https://www.accessdata.fda.gov/drugsatfda_docs/label/2006/021527s005lbl.pdf
- Lasmar LBF, Camargos PAM, Goulart EMA, Sakurai E. Risk factors for multiple hospital admissions among children and adolescents with asthma. J Bras Pneumol. 2006;32(5):391–9.
- Aggarwal S, Cepalo T, Gill S, Thipse M, Clifton KL, Higginson A, et al. Factors associated with future hospitalization among children with asthma: a systematic review. J Asthma. 2023;60(3):425–45. Available from: https://doi.org/10.1080/02770903.2022.2093127
Explorar
Artículos
Volúmenes
Sobre la revista
Más leídos
Emergencias Pediátricas
Emergencias Pediátricas
Emergencias Pediátricas
1º Congreso Mundial de Emergencias Pediátricas
Emergencias Pediátricas
Una nueva mirada a la vía aérea pediátrica: secuencia de intubación diferida como alternativa segura en situaciones de urgencias
Emergencias Pediátricas