Artículo original
Vol. 5 Núm. 2 (English)
15 min
Acute peripheral facial palsy in the pediatric age group: a retrospective observational study in a tertiary care hospital
Parálisis facial periférica aguda en edad pediátrica: un estudio observacional retrospectivo en un hospital de tercer nivel
Marta Vega-Bayón1*, Patricia Justo-Vaquero1, José-Manuel Marugán-de-Miguelsanz1, Jorge Carranza-Ferrer1, María de-Felipe-Pérez2
1Clinical University Hospital of Valladolid, Valladolid, Spain. 2Hospital de Medina del Campo, Medina del Campo, Valladolid, Spain
Correspondencia:
Recepción:
29/09/2025
Aceptación:
23/01/2026
Publicación:
26/06/2026
Métricas
68
Visualizaciones
3
Descargas
Compartir
Compartir
Resumen (EN)
Objective: To analyze the demographic and clinical variables of pediatric patients with acute peripheral facial palsy (APFP), as well as to compare our results with those reported in national and international studies.
Methods: An observational, descriptive, case-series study was conducted. Children under 14 years of age who presented to the emergency department with APFP from January 2015 to May 2024 were included.
Results: Thirty-eight patients were enrolled. The majority (60.5%) were girls, with a mean age at diagnosis of 8.6 years. In 24 (63.1%) cases, the cause was idiopathic. Case frequency was higher in summer (32.4%) and autumn (31.6%), followed by winter (18.4%) and spring (15.8%). Only 4 (10.5%) patients required complementary testing. Upper respiratory tract symptoms and headache (21.05%) were the predominant associated symptoms, followed by otalgia (15.8%). Nineteen cases (50%) corresponded to grade III on the House-Brackmann scale, 7 to grade II (18.4%), and 6 to grade IV (15.8%). Complete recovery was observed in 34 children (89.5%). Although all patients received corticosteroids, recurrence was observed in 1 (2.6%), and complete recovery was not achieved in 4 (10.5%), of whom 3 (75%) took more than 72 hours to start treatment and only 2 patients (50%) attended rehabilitation. No increase in cases was observed during or after the SARS-CoV-2 pandemic, with an annual mean of 4.16 pre-pandemic cases and 4.25 post-pandemic cases.
Conclusion: We describe a consecutive series of pediatric APFP, with no increase in cases during or after the SARS-CoV-2 pandemic, predominantly of idiopathic etiology, with no seasonal pattern, and with favorable progression following corticosteroid therapy; physical therapy proved useful in cases with incomplete recovery.
Palabras clave (EN):
Resumen (ES)
Objetivo: Analizar variables poblacionales y clínicas de pacientes pediátricos con parálisis facial periférica aguda (PFPA), además de comparar nuestros resultados con los reportados en estudios nacionales e internacionales.
Métodos: Se realizó un estudio observacional, descriptivo y de tipo serie de casos. Se incluyeron los niños menores de 14 años que acudieron al Servicio de Urgencias por PFPA desde enero de 2015 hasta mayo de 2024.
Resultados: Se reclutaron 38 pacientes. La mayoría (60,5%) niñas, con una edad media al diagnóstico de 8,6 años. En 24 (63,1%) la causa fue idiopática. La frecuencia de casos fue mayor en verano (32,4%) y otoño (31,6%), seguidas de invierno (18,4%) y primavera (15,8%). Únicamente 4 (10,5%) pacientes requirieron la realización de pruebas complementarias. El cuadro catarral y la cefalea (21,05%) constituyeron los síntomas asociados predominantes, seguidos por la otalgia (15,8%). 19 casos (50%) correspondieron a un grado III en la escala de House-Brackmann, 7 a un grado II (18,4%) y 6 a un grado IV (15,8%). Se constató la recuperación completa en 34 niños (89,5%). Aunque a todos los pacientes se les administró corticoesteroides, se observó recurrencia en 1 (2,6%) y no se logró la curación completa en 4 (10,5%) de los cuales 3 (75%) tardaron más de 72 horas en comenzar el tratamiento y únicamente 2 pacientes (50%) acudieron a rehabilitación. No se observó un incremento de casos durante ni después de la pandemia de SARS-CoV-2, con una media anual de 4,16 casos prepandemia y 4,25 casos postpandemia.
Conclusión: Se describe una serie consecutiva de PFPA pediátrica, sin incremento de casos durante ni tras la pandemia por SARS-CoV-2, de etiología mayoritariamente idiopática, sin patrón estacional y con buena evolución tras corticoterapia, siendo la fisioterapia útil en los casos con recuperación incompleta.
Palabras clave (ES):
Introduction
Acute peripheral facial palsy (APFP) is a weakness or paralysis of the facial muscles caused by a lesion of the facial nerve (cranial nerve VII) on its path from its nucleus of origin in the pons to the periphery, which produces an inability to voluntarily move the muscles of facial expression on the affected side. This pathology is frequently diagnosed in the emergency department, and its consequences can affect the social and emotional development of children(1). Therefore, it is important to know its characteristics and evolution to provide adequate care. This palsy is classified according to its etiology into idiopathic (also called Bell’s palsy), infectious, traumatic, neoplastic, and immune(2). The diagnosis of the idiopathic form is clinical, after the exclusion of other causes(2). Although it is sometimes necessary to resort to complementary tests such as analytical studies, cerebrospinal fluid studies, serologies, or imaging tests. The therapeutic approach includes general measures (artificial tears, ophthalmic ointment, and nocturnal occlusion), as well as early corticosteroid therapy, although its indication is controversial. In some patients, antivirals, antibiotics, or, in selected cases, surgical treatment may be necessary.
The study was proposed, in part, to delve into the care and follow-up needs of patients with this pathology in our hospital, since we did not find many studies carried out in centers with the same characteristics that addressed the follow-up of cases after diagnosis in the emergency department.
The objective of this study was to comprehensively characterize the cases of APFP treated in children under 14 years of age in the Emergency Department of a tertiary care hospital. For this purpose, their epidemiological characteristics (age, sex, and location), identified etiology, accompanying symptoms, degree of facial involvement, the use of complementary tests, therapeutic strategies applied, the need for referral to other specialists, and subsequent clinical evolution were analyzed. And finally, to compare the results obtained with national and international records to assess the representativeness of the local cohort.
Material and Methods
An observational, retrospective, and descriptive study was conducted, as well as a bibliographic review and update on the subject.
All children aged 0-13 years (both inclusive) who attended the Pediatric Emergency Department of a tertiary hospital between January 1, 2015, and May 31, 2024, diagnosed with APFP by a pediatrician at the time of evaluation, regardless of their time of evolution, laterality, or existence of recurrences, were included. The impossibility of guaranteeing clinical follow-up was not a reason for exclusion for the initial inclusion of patients in the study.
Cases with incomplete clinical histories, pathologies that could interfere with clinical evaluation, and patients without diagnostic confirmation were excluded from the study.
Data were extracted retrospectively from the “JIMENA version 3” digital clinical history system by searching for the diagnostic code of “peripheral facial palsy” in emergency episodes and statistically analyzed with the IBM SPSS Statistics for Windows program.
Data were collected on the epidemiology, etiology, clinical features, diagnosis, treatment, and resolution of each case. At the time of conducting the study, an attempt was made to contact the parents or guardians of the patients by telephone to learn about their subsequent clinical evolution after their visit to the Emergency Department. Parents received verbal information about the project.
For the assessment of impairment, two scales were used (available in annexes); in all patients, the House-Brackmann scale(3), a facial function grading scale that classifies into six grades (I-VI), where I is normal function and VI is total paralysis, and complementarily in some cases the Sunnybrook facial classification scale(4) was also used, a numerical scale from 0 to 100 subdivided into various sections (movement, well-being, oral, eye, lacrimal, and social) where 100 is considered normal.
According to the center’s own APFP protocol for pediatric emergencies, developed in 2018 jointly with the otorhinolaryngology service, patients are initially referred to the otorhinolaryngology service from pediatric emergencies, with this unit being responsible for subsequent referral to neuropediatrics if deemed necessary.
In addition, a structured search for articles related to childhood facial paralysis was carried out in PubMed and Cochrane.
This study has the approval of our hospital’s ethics committee.
Results
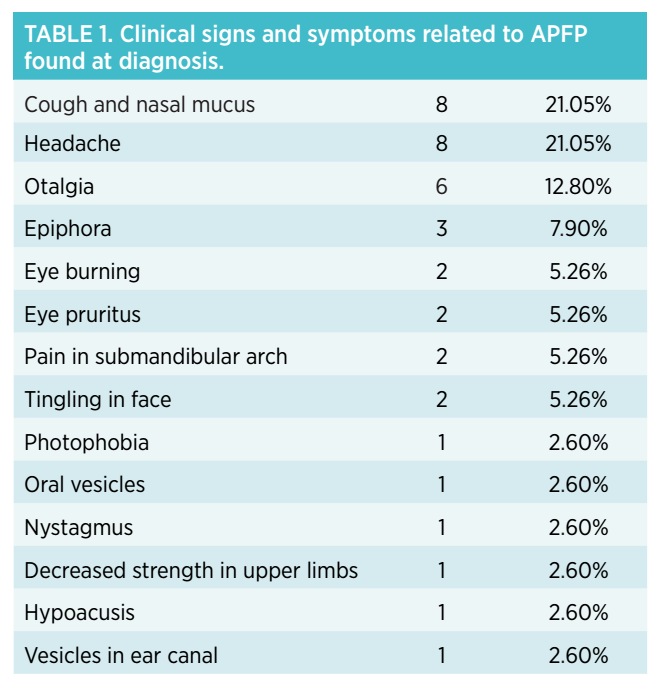
Thirty-eight children with a diagnosis of APFP were included, with a mean age at diagnosis of 8.6 years, of whom 23 (60.5%) were girls. In 55.2% of cases, the involvement was on the right side. The etiology was unknown in most cases (24 children; 63.15%). In the rest of the patients, facial paralysis was associated with cold symptoms (8; 21%), acute otitis media (6; 15.8%), mild head trauma (1; 2.6%), Ramsay Hunt syndrome (1; 2.6%), and Melkersson-Rosenthal syndrome (1; 2.6%), with the coexistence of respiratory or otological infectious processes observed in several patients at the time of diagnosis. The frequency of cases was higher in summer (32.4%) and autumn (31.6%), followed by winter (18.4%) and spring (15.8%). Clinical signs and symptoms related to APFP are reflected in Table 1. Nineteen cases (50%) corresponded to grade III on the House-Brackmann scale, 7 to grade II (18.4%), and 6 to grade IV (15.8%); in the remaining 6 cases, the severity was classified intermediately, assigning combined grades (e.g., II–III) when the involvement did not clearly fit a single category. The only case with recurrences after resolution of the condition corresponded to a Melkersson-Rosenthal syndrome. Only 4 of the 38 cases (10.5%) required complementary tests. In three children (7.9%), blood analysis was performed: one for acute otitis media with intense otalgia and lack of improvement after 48 hours of antibiotics, another due to suspected Melkersson-Rosenthal syndrome, and a third because of treatment with valproic acid to rule out pharmacological toxicity. Three other patients (7.9%) required a computed axial tomography scan, two of them corresponding to the previously mentioned patients with acute otitis media without improvement and Melkersson-Rosenthal syndrome, and the other for head trauma the previous day. Finally, one child (2.6%) required a lumbar puncture in the context of Melkersson-Rosenthal syndrome.
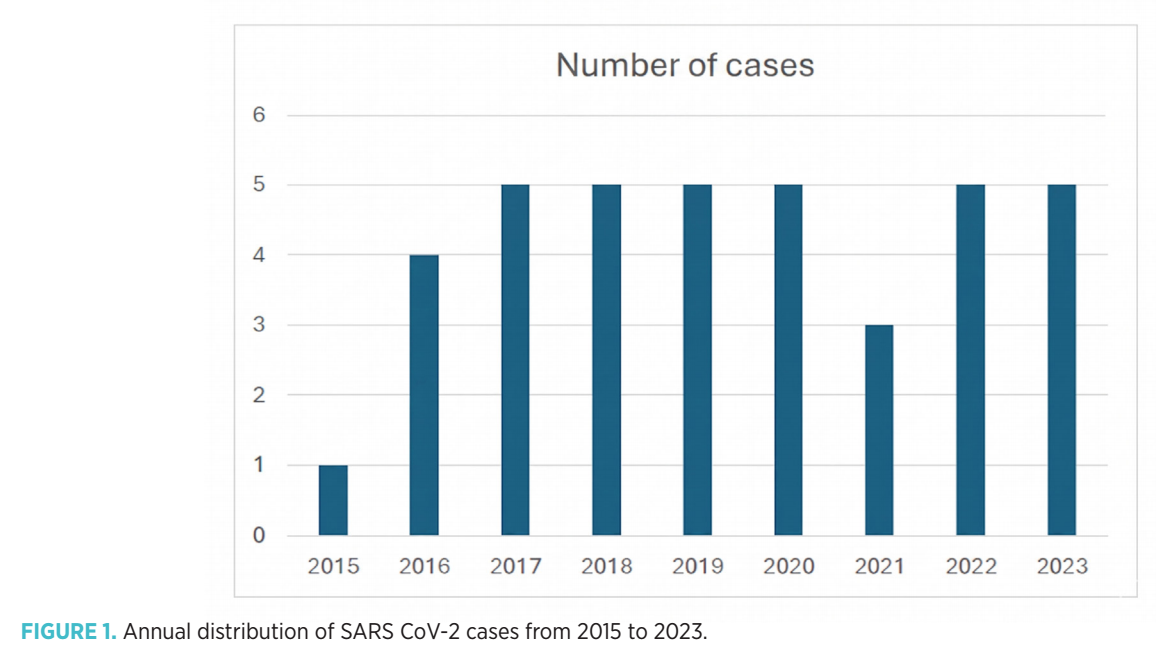
All patients (100%) received corticosteroid treatment after their emergency evaluation; most of them (58%) received treatment with prednisone, and the rest with prednisolone. The median duration of treatment was 10.2 days. Twenty-four (63.15%) at a dose of 2 mg/kg/day with a tapering schedule, 9 (23.7%) at 1 mg/kg/day, and 5 (13.15%) at 3 mg/kg/day; the dose variation is due to the introduction in 2018 of an action protocol for facial paralysis in which a dose of 2 mg/kg/day was established. In addition, two patients (5.3%)—corresponding to a case of Ramsay Hunt syndrome and another of Melkersson-Rosenthal syndrome—required antiviral treatment with acyclovir, and 2 others (5.3%) required antibiotic treatment, indicated in two cases of otitis with intense otalgia. Twenty-seven patients (71%) were referred to other specialties, mainly Otorhinolaryngology (96.3%) according to our hospital protocol and one case (2.6%) to Ophthalmology. Data on clinical evolution were obtained by telephone interview in 26 patients (68.4%): 7 (26.9%) recovered total functionality in the first week after their emergency visit, 6 patients (23.1%) in the second week, 3 patients (11.5%) in the third week, and 6 patients (23.1%) required four weeks to recover. Four children (15.4%) did not achieve a complete cure; of these, two corresponded to grade III on the House-Brackmann scale and the other two to grade IV, presenting sequelae after treatment, mostly (75%) a slight oral asymmetry with movement. Although of these 4, only 2 (50%) received rehabilitative treatment. Of the patients studied, only 2 (5.3%) required hospital admission; one was diagnosed with Melkersson-Rosenthal syndrome, while the other case corresponded to suppurative otitis media that required intravenous antibiotic therapy. Figure 1 shows the annual distribution of cases from 2015 to 2023, without noticing an effect of the SARS CoV-2 pandemic.
Discussion
APFP is a common reason for consultation in Emergency Departments and can affect the child’s social and emotional sphere. Although in most cases a specific cause is not identified(5), it can also originate from infectious processes, trauma, neoplasms, or immune alterations.
In our case series, as in the literature, idiopathic was the most frequent cause followed by infectious causes(6), mainly respiratory infections and acute otitis media.
In two patients, we had two characteristic syndromes. The first met the diagnostic criteria for Ramsay Hunt syndrome(7), a condition related to the varicella-zoster virus characterized by a specific clinical triad (facial paralysis, otalgia, and vesicles in the ear canal). The second case presented a more complex picture with recurrent facial paralysis, orofacial edema, and neurological manifestations (intense headache and altered sensitivity of the lower extremities), leading to suspicion of central pathology. However, neuroimaging and cerebrospinal fluid studies ruled out this possibility, and the suspected diagnosis was Melkersson-Rosenthal syndrome(8), this being the only case of recurrent facial paralysis.
Although in most cases the diagnosis of idiopathic facial paralysis can be established clinically through a detailed history, on occasions—as occurred in our series—it is necessary to carry out complementary tests to rule out secondary forms associated with potentially serious and treatable processes(9).
The imaging test of choice is magnetic resonance imaging (MRI) with or without contrast, indicated when atypical findings exist (bilaterality, fluctuation, progression of symptoms beyond the first 72 hours after onset, or recurrent facial paralysis)(10), additional neurological signs, progressive evolution, if secondary causes such as tumors are suspected(11), or when the condition does not show clinical resolution after a period of 3 to 6 months(12). CT is indicated in the presence of a history of craniofacial trauma, suspected fracture of the temporal bone, or in children with facial paralysis associated with otitis media when there is clinical deterioration, lack of improvement after 48 hours of appropriate antibiotic treatment, or suspicion of complications such as mastoiditis, intracranial extension, subperiosteal abscess...(13).
Indications for requesting laboratory analysis include the presence of systemic symptoms, suspicion of systemic causes, if the patient is younger than 6 months or presents an atypical course such as bilateral facial paralysis, relapses, or when other associated neurological deficits exist(14). In addition, in endemic areas or with a history of exposure, serology for Borrelia (Lyme disease) should be requested, especially if systemic symptoms or compatible epidemiological history are present.
The results obtained do not indicate a clear association between facial paralysis and seasonal cold exposure. A multicenter study(15) points out that the risk of acute facial paralysis is mainly related to sudden atmospheric changes, especially variations in barometric pressure and temperature, rather than seasonality. Consequently, the risk appears to depend on these climatic fluctuations regardless of the time of year. In our series, no seasonal preference was observed either, with a predominance of cases in spring and summer.
The data from our series coincide with what is described in the literature regarding the most frequent degrees of facial paralysis, including the study conducted in 2021 with 96 patients(16), which also identifies House-Brackmann grades 2 and 3 as the most common.
Regarding the evolution of facial paralysis, various studies have pointed out that treatment with corticosteroids in initial phases can shorten the healing time in patients older than 16 years treated within the first 72 hours(17), and multiple randomized controlled trials and meta-analyses have supported its efficacy in improving complete recovery rates. However, a recent randomized trial conducted in children under 18 years of age found no difference between oral corticosteroids and placebo in recovery rates at 3 months, 6 months, and 1 year, without recording serious adverse effects(10). In this context, the debate persists about the universal indication of corticosteroids in the pediatric age group, given that some studies indicate that up to 90% of children under 14 years of age show complete spontaneous recovery(10).
In our series, 32 patients (84.2%) showed complete recovery of facial function one month after starting corticosteroid treatment, a result that agrees with data previously described in the literature(10,18). However, it is worth considering that there are clinical indicators of poor prognosis for a complete spontaneous recovery, among which bilateral involvement and the presence of more severe symptoms stand out, according to the Sunnybrook or House- Brackmann assessments(10). In our series, sequelae were observed in four patients: two with grade III involvement and two with grade IV, coinciding with the findings described previously.
Although most patients with APFP recover completely, long-term sequelae can occur. In our sample, 4 (15.4%) presented sequelae. Among these, 3 (75%) took more than 72 hours to start treatment, which suggests that the early use of corticosteroids in certain cases could prevent the development of future sequelae. A meta-analysis showed that the early use of corticosteroids significantly decreases the proportion of patients with incomplete recovery of facial nerve motor function at 6 months or more and the incidence of motor synkinesias during follow-up(19).
On the other hand, only 2 of the 4 patients started physiotherapeutic rehabilitation, showing a notable improvement within a few weeks, which coincides with recent evidence suggesting that physiotherapy can favor functional recovery in peripheral facial paralysis, assessed using tools such as the Sunnybrook scale. Although available reviews—including a 2011 Cochrane review and a subsequent systematic review based on randomized or quasi-randomized trials—provide only weak evidence of its efficacy in achieving complete recovery or improvement, these data support the recommendation to refer patients who do not reach total recovery to physiotherapy, despite the fact that precise indications on the optimal timing of referral or the most appropriate therapeutic regimen do not yet exist(10).
Finally, and after being suggested in different articles a possible causality between COVID-19 and facial paralysis(20), we analyzed our sample without appreciating a significant increase in cases during and after the pandemic, with an average of 4.16 annual cases pre-pandemic and 4.25 post-pandemic.
Conclusions
We present a series of consecutive cases with APFP in childhood, without appreciating a significant increase during and after the pandemic by SARS-CoV-2. Most were of unknown cause, without a defined seasonal pattern, and had a complete recovery after initial treatment with corticosteroids. Physiotherapy was beneficial for patients who performed it due to incomplete recovery.
Funding
No funding was received for the research, authorship, and/or publication of this article.
Authorship contributions
Marta Vega Bayón: Formal analysis, Project administration, Investigation, Writing – review and editing, Data curation, Conceptualization, Writing – original draft, Methodology
Patricia Justo Vaquero: Writing – review and editing
Jose Manuel Marugán de Miguelsanz: Writing – review and editing
Jorge Carranza Ferrer: Writing – review and editing
María De Felipe Pérez: Writing – review and editing
Conflicts of interest
The authors declare that there is no commercial or financial conflict of interest for this research.
Use of artificial intelligence tools
I declare that no artificial intelligence tool (such as ChatGPT, Copilot, Gemini, or others) has been used in the writing, analysis, or review of this article.
References
- Derise N, Birgfeld C, Byrne P, Lu GN. Facial Nerve Pathology in Children. Oral Maxillofac Surg Clin North Am. 2024; 36(3):401-409.
- Torres Mohedas J, Vidal Estéban A. Parálisis facial (parálisis de Bell) (v.2/2021). Guía-ABE. Infecciones en Pediatría. Guía rápida para la selección del tratamiento antimicrobiano empírico [en línea][actualizado el 02-jun-2021; consultado el dd-mmm-aaaa]. Disponible en http://www.guia-abe.es.
- Huang B, Zhou ZL, Wang LL, Zuo C, Lu Y, Chen Y. Electrical response grading versus House-Brackmann scale for evaluation of facial nerve injury after Bell’s palsy: a comparative study. J Integr Med. 2014;12(4):367-71.
- Jirawatnotai S, Jomkoh P, Voravitvet TY, Tirakotai W, Somboonsap N. Computerized Sunnybrook facial grading scale (SBface) application for facial paralysis evaluation. Arch Plast Surg. 2021;48(3):269-277.
- Craig Zaidman, MD. (2024). Facial nerve palsy in children. Douglas R Nordli, Richard P Goddeau (Ed.), UpToDate. Acceso el 26 de diciembre de 2024. Facial nerve palsy in children
- Psillas G, Antoniades E, Ieridou F, Constantinidis J. Facial nerve palsy in children: A retrospective study of 124 cases. J Paediatr Child Health. 2019;55(3):299-304.
- Maharaj S. A Case Report of Infantile Ramsay Hunt Syndrome. Indian J Otolaryngol Head Neck Surg. 2022; 74(Suppl 1):384-386.
- Pavuluri A, Smith S, Narsinghani U. Rare diagnosis of Melkersson-Rosenthal syndrome in a paediatric patient. BMJ Case Rep. 2021; 14(6):e238431.
- Tankeré F, Hervochon R. Parálisis facial periférica. EMC-ORL. 2023, 52 (1): 1-22.
- Sarah N. Dalrymple, MD, Jessica H. Row, MD, John D. Gazewood, MD. Bell’s palsy. Primary Care: Clinics in Office Practice, 2025-03-01, Volumen 52, Número 1, Páginas 111-121, 2024 Elsevier Inc.
- Tanya J. Rath, MD. Bruno Policeni, MD, MBA. Amy F. Juliano, MD. ACR Appropriateness Criteria Cranial Neuropathy: 2022 Update. Journal of the American College of Radiology. Volume 19, Issue 11, supplement, S266-S303, Nov 2022.
- Baugh RF, Basura GJ, Ishii LE, et al. Clinical Practice Guideline. Bell’s Palsy. Otolaryngology-Head and Neck Surgery. 2013;149: S1-S27.
- Mohit Agarwal, MD. Amy F. juliano, MD. M. Reza Taheri, MD. David Zander, MD. Et al. ACR Appropriateness Criteria Inflammatory Ear Disease. Journal of the American College of Radiology. Volume 22, Issue 5, Supplement, S300-S318, May 2025.
- Dalrymple SN, Row JH, Gazewood J. Bell Palsy: Rapid Evidence Review. Am Fam Physician. 2023 Apr;107(4):415-420. Erratum in: Am Fam Physician. 2024 Feb;109(2):105.
- Franzke P, Bitsch A, Walther M, Schiffner R, Rupprecht S, Rasche M, Volk GF, Witte OW, Schlattmann P, Guntinas-Lichius O, Hagemann G, Schwab M, Rakers F. Weather, Weather Changes and the Risk of Bell’s Palsy: A Multicenter Case-Crossover Study. Neuroepidemiology. 2018;51(3-4):207.
- Bylund N, Hultcrantz M, Jonsson L, Marsk E. Quality of Life in Bell’s Palsy: Correlation with Sunnybrook and House-Brackmann Over Time. Laryngoscope. 2021;131(2):E612-E618.
- Nakano H, Fujiwara T, Tsujimoto Y, Morishima N, Kasahara T, Ameya M, Tachibana K, Sanada S, Toufukuji S, Hato N. Physical therapy for peripheral facial palsy: A systematic review and meta-analysis. Auris Nasus Larynx. 2024;51(1):154-160.
- Madhok VB, Gagyor I, Daly F et al. Corticosteroides para la parálisis de Bell (plastia facial idiopática). Sistema de base de datos Cochrane. Rev. 2016; 7: CD001942.
- Madhok VB, Gagyor I, Daly F, Somasundara D, Sullivan M, Gammie F, Sullivan F. Corticosteroids for Bell’s palsy (idiopathic facial paralysis). Cochrane Database Syst Rev. 2016 Jul 18;7(7):CD001942.
- Hogg ES, Hampton T, Street I, Clarke R, Wright K, De S, Sharma SD. Increased incidence of idiopathic paediatric facial palsy during the coronavirus disease 2019 pandemic. J Laryngol Otol. 2021;135(8):668-670.
Explorar
Artículos
Volúmenes
Sobre la revista
Más leídos
Emergencias Pediátricas
Emergencias Pediátricas
Emergencias Pediátricas
1º Congreso Mundial de Emergencias Pediátricas
Emergencias Pediátricas
Una nueva mirada a la vía aérea pediátrica: secuencia de intubación diferida como alternativa segura en situaciones de urgencias
Emergencias Pediátricas